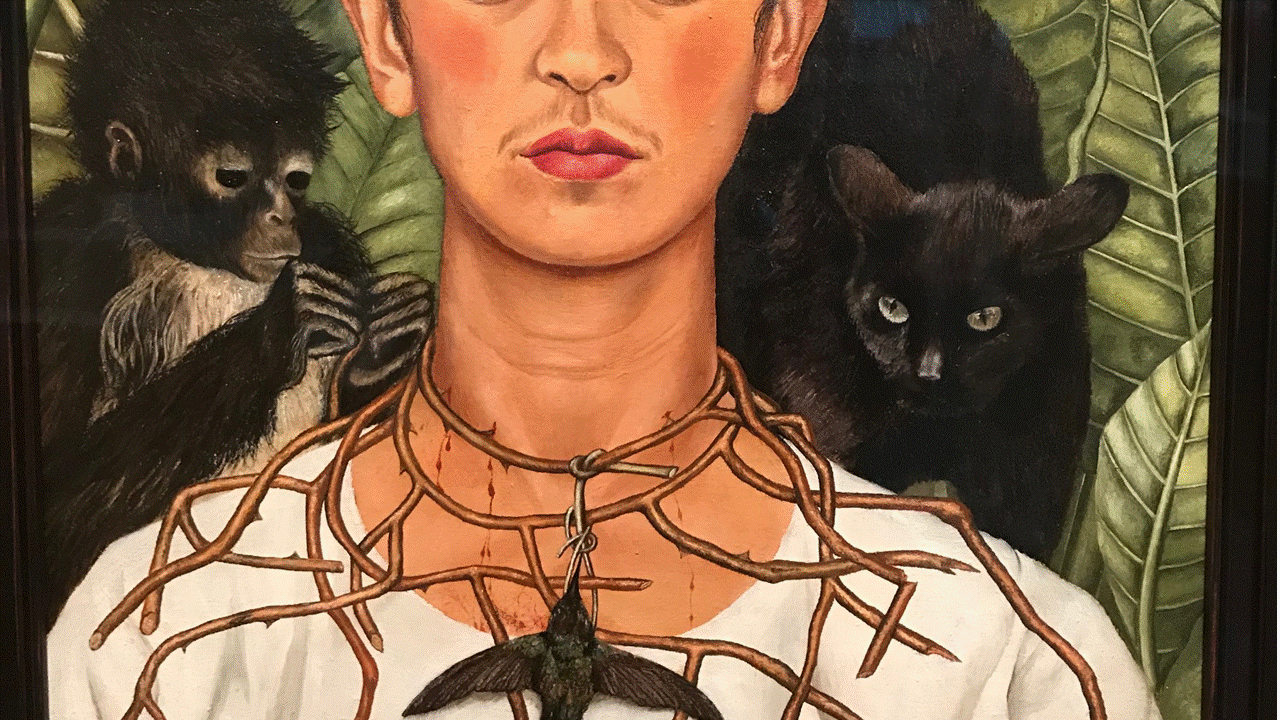Dr. Honey’s book, The Tenth Nerve, has been published by Penguin Random House Canada. It is available at Amazon, Indigo, local bookstores and drchrishoney.com. The book is an homage to several patients who taught him more about medicine than any lecture or textbook.
Show on Home
World Congresses held in Vancouver
The 16th World Congress of the International Neuromodulation Society (INS) was held in Vancouver May 2024. Professor Honey was the Chairman of the Congress and hosted 1,300 clinicians and researchers.
The 3rd World Congress on MVD neurosurgery was hosted in Vancouver July 2022. Dr. Honey was the President of this Society (2019-2022) and hosted the meeting.
Please see our WEBSITE for the INS World Congress, May 11-16, 2024
DBS Clinic
After implantation of the deep brain stimulator (DBS), the stimulation can be adjusted to maximize the benefits and minimize any side effects. This adjustment of the stimulator is done in the DBS clinic using a very small hand-held computer which rests on top of your shirt. The DBS clinic is located on the eighth floor of the Diamond Healthcare Center at Vancouver General Hospital (2775 Laurel St.).
Here as a link to some useful information for patients attending the DBS clinic.
In the DBS clinic, you will meet our DBS nurses: Mini, Nancy, Natasha and Jessica.
VANCOUVER syndrome
Our team successfully operated on the first case in the world where a neurogenic cough was cured by a unilateral decompression of the vagus nerve (MVD surgery). We hope this new syndrome will become known as Vagus Associated Neurogenic Cough Occurring due to Unilateral Vascular Encroachment of the Root. This acronym, VANCOUVER syndrome, is an homage to the city where this discovery was made.
Here is a link to our original paper published in the Journal of Otology, Rhinology & Laryngology.
Here is a link to our recently published paper in the Frontiers of Neurology.
What is Neurogenic Cough?
Neurogenic cough is a chronic cough caused by changes in the nerves of the throat or lungs. It is not caused by any of the usual causes of chronic cough such as gastric reflux, asthma, eosinophilic bronchitis, post-nasal drip, rhinosinusitis, or medications. Some cases of neurogenic cough are due to nerve damage or hypersensitivity following a viral illness.
We believe that some cases of neurogenic cough can be caused by a blood vessel pinching or compressing the vagus nerve. This is VANCOUVER syndrome.
How does VANCOUVER syndrome cause cough?
The analogy we use for the tickling sensation in your lungs that causes chronic cough in VANCOUVER syndrome is the tingling sensation in your hand that occurs when you hit your ‘funny bone’ – or bang your ulnar nerve at the elbow. There is nothing wrong with your hand but the nerve from your hand (the ulnar nerve) has been hit at the elbow and sends signals to the brain which are interpreted as tingling in your hand. The same thing can happen with your vagus nerve. If the vagus nerve is hit or pinched, it will send signals to the brain which are felt like a tickling sensation in your lungs. The vagus nerve normally carries a tickling sensation from the lungs and only fires when a foreign object enters the lungs. This is the normal cough reflex. If the vagus nerve fires inappropriately – not because something entered the lungs but rather because the nerve itself was pinched- you get VANCOUVER syndrome. The brain interprets the signals coming from the ‘pinched’ vagus nerve as a tickling sensation in the lungs and triggers a cough.
We can potentially cure this chronic cough by finding where the vagus nerve is pinched and decompressing it. There could be a lot of people with neurogenic cough that do not have VANCOUVER syndrome and we want to be sure we do not operate on them. Over the last two years we tried a variety of tests and believe the appropriate diagnostic tests are as follows:
How to Diagnose VANCOUVER Syndrome
Patients with VANCOUVER syndrome describe an intermittent tickle deep in their throat or chest. The sensation triggers an irresistible cough. The symptoms can get better with anti-neuralgia medications – the same medications that would help trigeminal neuralgia (e.g. carbamazepine, gabapentin). Our diagnostic protocol (click for paper) has been published and we use 1. MRI and 2. inhaled nebulized lidocaine as screening tests.
The initial screening test is an MRI to look for the compression or pinch of the vagus nerve. If there is no compression of the nerve, there is no VANCOUVER syndrome. If there is a compression of the vagus nerve then it COULD be VANCOUVER syndrome and an additional screening test is needed. There are some people who have what looks like a vagus nerve compression on the MRI but are completely asymptomatic – a compression of the vagus seen on the MRI is therefore necessary but not sufficient for a diagnosis of VANCOUVER syndrome. The next screening test is inhaled lidocaine.
Lidocaine is a local anesthetic and can stop a nerve from transmitting its signals. Inhaled nebulized lidocaine should stop the tickling sensation by anesthetizing the vagus nerve endings in the throat and lungs. With no tickling sensation, the coughing should stop for the duration of the anesthetic (an hour or so). This is a relatively simple test, familiar to most ENT specialists, and we use this as the second screening test. If that test works (i.e. the sensation to cough is gone for the duration of the anesthetic), then we proceed with more sophisticated tests to determine if you have VANCOUVER syndrome. If that screening test does not work, we know the patient does not have VANCOUVER syndrome.
The next step is to determine which vagus nerve is affected. There is a right and left vagus nerve and it is very likely that only one is compressed. Some patients can feel which side the tickling sensation is coming from. If that side corresponds to the side with the vagus compression seen on MRI, then the patient can consider surgery (see MVD surgery below). If the patient can not feel which side is affected, then we use a vagus nerve block to confirm the affected side.
Our protocol for unilateral vagus nerve block has been published (click for paper). We determine which vagus is affected by anesthetizing one at a time. When a vagus nerve is anesthetized, it can no longer send tickling information to the brain. It also can not send information to the vocal cords and so the voice is temporarily hoarse. Patients have a unilateral vagus nerve block (ultrasound guided procedure in the neck). If the patient’s voice becomes hoarse then we know the vagus nerve has been anesthetized successfully. If the tickling sensation and coughing stops then we know it was that vagus nerve causing the cough. When the voice returns to normal as the anesthetic wears off (about 90 minutes later), the coughing should return. A week later, the patient returns to have the other side done – this should have no benefit on the cough because VANCOUVER syndrome is one sided. We use this extra test to be certain the problem is one-sided. If there is a blood vessel compressing the vagus nerve on the same side that the anesthetic was effective, then we will consider offering surgery to try and cure the condition. The surgery is called microvascular decompression of the vagus neve or MVD of the Xth nerve.
Surgery
MVD is a common neurosurgical proceed used to decompress the trigeminal nerve for trigeminal neuralgia or the facial nerve for hemi-facial spasm. Our centre has performed over 1,000 of these operations for these two conditions. The same principles are used to decompress the vagus nerve for VANCOUVER syndrome. The risks of MVD are best discussed directly with your neurosurgeon as results will vary depending on their experience.

The Haida artist, Bill Reid, carved The Raven and the First Men and it is on display at the Museum of Anthropology in Vancouver. It depicts the Haida’s interpretation of human creation. I believe this statue is also symbolic of the birth of VANCOUVER syndrome. A condition that has been around a long time but only recently recognized.
Information for Physicians
Cautery During Surgery
Patients with DBS occassionally need other operations. We are quite proud that many of our patients have gone on to require hip and knee replacements because of their increased mobilization after DBS. Surgeons should use bipolar cautery if possible. In an article in the British Journal of Anesthesia (2005) 95:424-427, Dr. Davies reported, “The manufacturers’ advice is to avoid electrocautery. If electrocautery is necessary, bipolar mode should be used. If unipolar electrocautery is essential, the ground plate should be kept as far away from the neurostimulator and leads as possible and positioned so that the pulse generator and leads are not situated between the surgical site and the ground plate.”
Information for surgeons (jump to page 20)
MRI
Patients with the new generation of Medtronic ACTIVA or PERCEPT products can have MRI investigations. There is a strict protocol to follow (see guidelines below). Patients with Boston Scientific or St. Jude/Abbott products have not yet been cleared for MRI. Our patients can call the DBS Clinic (604 875 4111 ext 69584) to find out what device they have implanted.
Phone Medtronic for help at 1 877 895 7226
Information about getting an MRI when you have Boston Scientific DBS
Avoid these drugs if you have Parkinson’s
The picture below was taken of the “Group of Seven” in 1920. The Canadian artists present (from left to right) were Fredrick Varley, A.Y. Jackson, Lawren Harris, (Barker Fairley was influential but not consider part of the gang), Frank Johnson, Arthur Lismer, and J.E.H. MacDonald. Franklin Carmichael, the youngest original member, was not pictured.

Hemi-Laryngopharyngeal Spasm (HeLPS syndrome)
Our sentinel paper describing the world’s first recognized case of HEmi-LaryngoPharyngeal Spasm or HeLPS was published in the Journal of Neurosurgery (in July 2016).
Here is a link to the paper
.
Our more extensive description of three additional cases of HELPS was published in the Journal of Neurosurgery (in July 2018).
Here is a link to the paper.
.
Our paper describing the MRI findings in HELPS was published in the American Journal of Neuroradiology (in Oct 2018).
Here is a link to the paper.
.
Our paper demonstrating the connection between glossopharyngeal neuralgia and HELPS was published in Neurosurgery (in December 2019). It also discovered 27 previous descriptions of patients with HELPS, unrecognized at the time, from six different countries in four different languages.
Here is a link to the paper.
.
Dr. Amanda Hu, in collaboration with Professor Murray Morrison, has published a paper reviewing the diagnosis of HELPS for otolaryngologists. This was published in 2020 in the Annals of Otology, Rhinology, & Laryngology.
Here is a link to the paper.
.
A link to our most recent paper was published in 2025 in the Frontiers of Neurology.
Here is a link to the paper.
.
HELPS syndrome
HELPS syndrome is a condition caused by a blood vessel pinching the nerve rootlets of the Vagus nerve (the Xth cranial nerve). It is similar to the well recognized hemifacial spasm syndrome but the nerve involved is the Vagus instead of the Facial nerve. As a result, the symptoms are episodic throat contractions and cough. The throat contractions typically become stronger and more frequent over the years and can lead to a terrifying inability to breath or choking sensation. Patients may end up in the Emergency Department being intubated or with a permanent tracheostomy because of their inability to breath during a severe episode. Some but not all of our patients can tell which side of their throat (left or right) contracts during a choking episode. In between these choking episodes, patients feel normal.
Physicians unfamiliar with this condition may misdiagnose HELPS syndrome as a psychiatric conversion disorder, a response to gastric reflux, or laryngeal dystonia. One identifying feature is that the spasms eventually occur while sleeping. Another feature of this condition is that it is associated with coughing episodes. These coughing spells usually begin as a response to a tickling sensation at the back of the throat. In response to this tickling sensation, the patient will cough. This coughing tends to get stronger over the years and eventually can be so severe that it causes dizziness (“seeing stars”), vomiting or urinary incontinence. Our patients have described various triggers for this coughing including environmental odors, prolonged or loud talking but it can also occur spontaneously without any obvious cause. Eventually the coughing will occur while sleeping.
Diagnosis
The diagnosis of HELPS syndrome requires a history of intermittent choking and coughing. We have published our guidelines for the diagnosis of this condition (see above paper). Obvious causes need to be excluded including acid reflux, exposure to airborn irritants, conversion disorder and dystonia. Laryngoscopy can sometimes see a unilateral twitch of a vocal fold following vocalization. This is pathognomonic and not seen in any other condition. The choking will be reduced by unilateral botulinum toxin (Botox) injections on the side of the problem but will have no effect on the opposite side. These tests should be spaced in time to give the vocal fold time to recover completely from the first injection before trying the second side. If there is a unilateral response to the Botox injections and an MRI demonstrates a vessel encroaching on the vagus nerve on the same side, then neurosurgery can be discussed.
Treatment
Patients can be treated with repeated Botox injections. The throat spasms will still occur but will be much less severe. These injections typically need to be repeated every three months. This will not stop the coughing because the tickling sensation continues. The coughing may respond to anti-neuralgia medications such as carbamazepine or amitriptyline. If patients want an opportunity for a definitive cure, then the pinched vagus nerve must be decompressed surgically. This operation is called a microvascular decompression (MVD). Many neurosurgeons will be familiar with the MVD operation for trigeminal neuralgia (Vth cranial nerve), hemifacial spasm (VIIth cranial nerve), or glossopharyngeal neuralgia (IXth cranial nerve). The operation is essentially the same except the nerve being decompressed is the Vagus (Xth cranial nerve).
During the world’s first successful operation to cure this condition, we saw that two of the rootlets forming the patient’s Vagus nerve were severely stretched by a loop of the posterior inferior cerebellar artery (see Figure 1 below). After we freed the rootlets from some scar tissue, one of them fell back into the normal position (see Figure 2 below). We then moved the artery slightly to free up the second rootlet (see Figure 3 below). The patient did well with no surgical complications and has not had another episode of HELPS in over 4 years.

Figure 1:
The top two of the five rootlets making up the Vagus nerve (cranial nerve X) in this patient were obviously distorted by the posterior inferior cerebellar artery. The glossopharyngeal nerve (cranial nerve IX) was not affected.

Figure 2:
After freeing up some scar tissue around the rootlets, one of them fell back into the normal position. We then moved the artery slightly to take the pressure off the other affected rootlet.

Figure 3:
At the conclusion of the operation, all the nerve rootlets were safely decompressed.
Listen to a patient describe their symptoms
We are very grateful to our patients for sharing their stories. In the video below, “Patient #2” describes his HELPS syndrome before and 8 months after MVD surgery.
.
Future Work
First, we are working to clarify the diagnosis of this condition. It is likely that patients will present with slight variations of symptoms and we want to understand what are the common themes (e.g. throat contractions and cough) and what are the less commonly associated problems (e.g. changes in voice or a feeling of a fat tongue). We also want to understand what is the best method of conclusively diagnosing this condition. We believe that the unilateral vocal fold twitch described in our paper is unique to this condition. Not all patients will have this (or it will not be present during the examination). A unilateral improvement in throat contractions following Botox with no improvement on the other side is suggestive of a unilateral problem. If the MRI shows a vessel encroaching on the vagus nerve on the same side then that is highly suggestive of HELPS on that side.
Second, we are working to educate our colleagues around the world that HELPS exists and can be cured. This will be done with publication of our work in peer-reviewed journals and presentations at scientific conferences. Our peer-reviewed papers (see above) are available for our colleagues to read and learn about HELPS syndrome. We have presented our first case to our North American neurosurgical colleagues at the American Society for Stereotactic and Functional Neurosurgery (ASSFN) in June 2016 and presented our first four cases to our European colleagues at the European Society for Stereotactic and Functional Neurosurgery (ESSFN) meeting in September 2016. Our first five cases were presented to the World Society for Stereotactic and Functional Neurosurgery (WSSFN) at their quadrennial meeting in Berlin June 2017 (on the last lecture of the final day of the meeting!). Dr. Honey has also presented this work as an invited guest at the 4th annual Russian Federation of Stereotactic & Functional Neurosurgery meeting in Moscow (May 2018) and as a guest of the Iranian Neurosurgical Society (May 2018).
Third, although the surgical cure will lie in the hands of neurosurgeons, the diagnosis (and thus access to care) will depend on our ENT and Emergency Medicine colleagues. We will have to educate them as well about HELPS. It is unfortunate that all our patients were told at one time during their illness that they had a psychiatric illness. This is a misdiagnosis but a common medical error when the physician does not recognize the illness. The stress of being misdiagnosed can lead to anxiety for our patients. They tend to avoid any food or activity that happened to precede their last severe episode and therefore they can develop some obsessive-compulsive traits. Finally, being told “it’s all in your head” can make some patients angry. The combination of anxiety, obsessive-compulsive traits and anger can mislead a psychiatrist into believing that the patient does have a psychiatric disorder. VANCOUVER syndrome is a physical illness and it has a surgical cure.
Ultimately, we need other centers to be able to recognize and treat this condition.
The picture below is a close-up of a self portrait by Frieda Kahlo entitled “Self portrait with thorn necklace and hummingbird” (Autorretrato con collar de espinas y colibrí ) from 1940. The constricting necklace reminds me of the throat contractions of hemi-laryngopharyngeal spasm.

Glossopharyngeal Neuralgia
This information is designed only to help patients talk with their physicians about Glossopharyngeal Neuralgia (GPN) and is not intended to provide treatment guidelines.
Introduction
Glossopharyngeal neuralgia is a very rare neurologic condition that causes intermittent, extremely painful, one-sided throat pain. It is exactly analogous to the much more common trigeminal neuralgia (where the pain is in the face) but the affected nerve is the glossopharyngeal instead of the trigeminal. Each glossopharyngeal nerve (there is one on the right and one of the left) is responsible for sensation in the back of the tongue and throat. That is why the pain is felt in the back of the tongue and throat. The pain is triggered by touching this area – i.e. by swallowing.
By 2015, we have seen well over a 1,000 patients with trigeminal neuralgia but only 14 with glossopharyngeal neuralgia. It is truly rare – a hundred times less common as trigeminal neuralgia.
The type of pain is identical to trigeminal neuralgia – “electrical bolts of lightning going down the back of my tongue” or “like swallowing shards of glass“. Only the location is different – it occurs in the throat not face. The pain is typically brief and lasts only a few seconds but the attacks can be multiple. Patients can mistakenly report that their pain is constant but it is really repeated bouts of intermittent pain. This is a very important distinction. I have seen two patients with truly constant pain in the throat that turned out to be a neuropathic deafferentation pain not GPN.
Rarely (less than half the time) patients with glossopharyngeal neuralgia get symptoms also related to the Vagus nerve. The Vagus nerve (cranial nerve X) is located immediately beside the glossopharyngeal and can be compressed by the same blood vessel. When the Vagus nerve is involved, patients can feel pain deep in their ear. Strong Vagus nerve involvement can cause profound slowing of the heart rate – these patients get episodes where they feel their throat pain and then suddenly lose consciousness (faint) because their heart stops for a moment! This unusual condition is sometimes called vago-glossopharyngeal neuralgia.
Patients with glossopharyngeal neuralgia can also sometimes (10%) have associated coughing and very rarely can also have choking episodes. Our team was the first to highlight this association in a recent peer-reviewed paper (see paper #2 in our publications).
We believe glossopharyngeal neuralgia occurs when the nerve losses its insulation (myelin). This most typically occurs when a blood vessel rubs against the nerve for many years. This blood vessel is typically the posterior inferior cerebellar artery or PICA. We believe the blood vessel wears away the insulation of the nerve and allows the nerve to ‘short-circuit’. Normally, touching the throat triggers a nerve impulse in a branch of the Vagus and that information travels down the ‘touch’ branch of the nerve to the brain and signals the throat has been touched. In Glossopharyngeal neuralgia, that nerve branch has lost its insulation and therefore the normal touch signal can ‘short-circuit’ into another branch of the nerve which normally carries pain signals. The swallowing therefore triggers a very painful sensation in the throat. Over the years, the condition will typically fluctuate with symptoms going away for several months (remission) and then returning again (relapse). The natural history of this condition is slow worsening – remissions get shorter and relapses get more severe over the years.
There are at least four other potential causes for the loss of myelin around the glossopharyngeal nerve.
The first is Eagle’s syndrome. This is a rare condition, known to most ENT specialists, where the nerve is caught against an abnormally long piece of bone sticking down from the bottom of the skull. The nerve rubs against the bone and is demyelinated causing glossopharyngeal neuralgia. This condition is diagnosed by a CT scan of the skull which shows the styloid bone is longer than 3 cm. The treatment is an ENT procedure to brake off that piece of bone.
The second is a tumor in the neck near the pathway of the glossopharyngeal nerve. This can be diagnosed with a CT scan using contrast dye. The treatment is directed towards treating the tumor/cancer by an ENT specialist.
The third is multiple sclerosis where the patient’s own immune system attacks the myelin. The loss of myelin may be inside the brain along the ‘pain pathway’ from the nerve to the trigeminal caudalis nucleus. This must be exceedingly rare – I have treated over 300 patients with multiple sclerosis and trigeminal neuralgia but can not remember one with GPN.
The fourth is a viral infection of the nerve. This usually causes demyelination resulting in the touch-induced electrical pain but ALSO causes nerve damage which can cause a sensation of constant pain (often burning) in the same area of the throat. This condition is extremely difficult to treat and usually requires a pain specialist. Long bouts of burning after a series of electric shock-like pain is common but constant burning 24/7 suggests a different diagnosis – glossopharyngeal neuropathic pain rather than glossopharyngeal neuralgia.
Medical Treatment
Just like trigeminal neuralgia, glossopharyngeal neuralgia can be treated with medications. The medications and rational are the same – anti-epileptic medications are used to try and stop the nerve from ‘short circuiting’. Patients can try a variety of medications under the supervision of their neurologist. There are many different medications that can be effective (e.g. carbamazepine (trade name: Tegretol), neurontin (Gabapentin), pregabalin (Lyrica)).
In general, if the medications can control your symptoms, there is no need for surgery. If the medications can not control your pain OR if the side effects of the medications are intolerable (e.g. sedation) then you are a potential candidate for surgery.
If the throat is numb, it usually can not trigger glossopharyngeal neuralgia. In the old days, ENT specialists used to confirm the diagnosis by putting a pledget soaked in cocaine in the back of the throat. This numbed the throat and typically blocked the glossopharyngeal neuralgia for the length of the anesthetic effect. The addictive properties of cocaine stopped the practice and now specialists use a local anesthetic such as Marcaine. Patients should discuss with their specialist if a topical anesthetic mouth wash could help them. As with every medication, caution is required and too much anesthetic can adversely affect the heart.
Surgical Treatment
The benefits and risks of surgery must be discussed directly with your neurosurgeon. The risks can vary between centres with different experience.
Just like trigeminal neuralgia, a microvascular decompression of the glossopharyngeal nerve will work in the vast majority of cases. Not all patients will be cured by the perfectly performed operation because the surgery just decompresses the nerve (by moving the blood vessel away) it does not remyelinate the nerve. We rely on the body to heal and remyelinate the nerve – which it can do in the vast majority of cases. Sometimes, however, the nerve is too badly damaged to heal and the pain continues. Unfortunately, there is often very little room around the nerve to push the vessel away from the nerve. Because the nerve and the vessel (held away from the nerve with a Teflon padding) often remain in close proximity, recurrent compression with recurrent painful symptoms is a problem with this operation. Some surgeons (including our team) recommend cutting the glossopharyngeal nerve instead of decompressing it. This reduces the chance of recurrence and is well tolerated by the patient.
When the upper fibres of the Vagus nerve are involved, the situation becomes more complex. Ideally, the surgery in those cases would also include cutting the upper sensory branches of the Vagal nerve. This was first recommended by the Stockholm team in 1962. Cutting any of the motor branches of the vagal nerve will cause difficulty swallowing and a hoarse voice. In order to avoid the motor branches of the vagal nerve, we have published our recommended method of special intraoperative monitoring (see paper #45 in our publications). Each rootlet of the Vagus nerve (there are typically 5 or 6) is tested to see if it causes a contraction of the throat before it is cut. We would recommend only cutting those branches which do not cause a throat contraction (i.e. spare all motor branches of the Vagus nerve). Our interest in glossopharyngeal neuralgia has provided new information on the neuroanatomy and physiology of the glossopharyngeal and Vagus nerves. We have recently published this work in peer-reviewed medical journals for the benefit of our colleagues (see paper #9 in our publications).
The picture below is a close-up from Sandro Botticelli’s “Spring” (Primavera) from the late 1470s. Chloris is being transformed into Flora (spring) and we see the side of her neck. This is the location of glossopharyngeal neuralgia which radiates down one side of the throat, much like the vine extending down her neck.


Post Herpetic Neuralgia (of the face)
This information is designed to help patients talk to their neurosurgeons about their facial pain. It is not intended to give specific treatment guidelines.
Introduction
There are many different pathologies that can cause pain in the region of the face. The most common causes are dental (e.g. sore tooth) and sinus pain (e.g. sinusitis). Our clinic has focused on the types of pains caused by neurological conditions. These include the following:
- trigeminal neuralgia
- post-herpetic neuralgia
- de-afferentation neuropathic pain
- cluster headache
- migraine
A more extensive list of the causes of facial pain includes the following:
- dental problems (e.g. cavities, tooth abcess, gum disease)
- skin problems (e.g. infections, trauma)
- muscle problems (e.g. deep infections, trauma, tumors)
- parotid gland problems (e.g. infection, stones)
- ear problems (e.g. infections)
- sinus problems (e.g. sinusitis, trauma, tumors)
- skull problems (e.g. infection, trauma, tumors)
- eye conditions (e.g. orbital infections or tumors)
- TMJ syndrome
- Neurological conditions (trigeminal neuralgia, post-herpetic neuralgia, nerve damage following dental misadventure or trauma, migraine, cluster headache)
Before you can begin treating a medical problem, you must understand its cause. This is true regardless of the medical condition but is absolutely crucial when dealing with facial pain. The perfect operation for trigeminal neuralgia will not help post-herpetic neuralgia. It is therefore vitally important that the first step in treating a facial pain condition is making the correct diagnosis.
Post-herpetic Neuralgia
Post-herpetic neuralgia (PHN) is caused by nerve damage following a bout of shingles. Usually the pain associated with the rash and skin blisters of shingles fades within a few weeks. If the pain continues after the rash has cleared (some say after 3 months) then the pain is called PHN. ‘Shingles’ is the lay term for a medical condition called herpes zoster. Shingles occurs when the chicken pox virus (varicella zoster) becomes activated for some reason after lying dormant in the body for many years. After a bout of chicken pox (usually as a child), the immune system clears the virus from the body but some continue to ‘live’ in nerve cells. No one knows why the virus can become active again decades later but the condition is much more common in those with a weaken immune system (e.g. the elderly). Since the virus is in a nerve cell, the resulting infection (shingles) typically follows the course of that nerve. The rash and blisters therefore occur in the dermatome of that nerve. For example, in the chest the rash follows the curve of the intercostal nerve as it hugs the ribs. In the face, the rash will follow one (or more) of the branches of the trigeminal nerve.
The incidence of PHN following shingles varies with age (more common if you are older) and with location (more common in the face). The pain is described as having two different qualities. The first is a constant burning that can vary in intensity but never goes away while awake. The second is an intermittent sharp or electrical pain that can be triggered by touch. Doctors should be careful to listen to the whole story of how the pain started and not just focus on the current condition. ‘Touch-induced electrical pain’ sounds a lot like trigeminal neuralgia. If you miss the fact that the pain began after a bout of shingles (not impossible if the pain began years ago) then you may incorrectly try to treat PHN as a case of trigeminal neuralgia.
The correct treatment of PHN will often require the ongoing care of a neurologist or pain specialist. There are a great many different treatments that can be tried (a sure sign that none of them have proven to be superior). A combination of topical creams to numb the area and systemic pills to down-regulate the nervous system will help the majority of patients. A few, however, will continue to be disabled by this chronic painful condition.
For those rare patients with pain that has continued for years despite adequate trials of all medications, surgery can be an option. If the pain is disabling the patient, then they deserve to understand the potential benefits and risks of surgery so that they can weigh the pros and cons of surgery against their current quality of life.
The Surgical Treatment of Facial PHN
The picture below is of a painting by Edvard Munch entitled “The Scream” (Der Schrei der Natur) and painted in 1893. It has come to be an iconic image of mankind’s anxiety and may represent how some patients with intractable pain come to feel when none of the medical therapies have worked for them.